Personal View The granting of emergency use designation to COVID-19 candidate vaccines: implications for COVID-19 vaccine trials
Jerome Amir Singh, Ross E G Upshur Summary
An efficacious COVID-19 vaccine is currently the world’s leading research priority. Several nations have indicated that if there is a compelling case for use of a vaccine before it is licensed, they would be prepared to authorise its emergency use or conditional approval on public health grounds. As of Dec 1, 2020, several developers of leading COVID-19 candidate vaccines have indicated that they have applied, or intend to apply, for emergency authorisation for their vaccines. Should candidate vaccines attain emergency use designation and be programmatically deployed before their phase 3 trials conclude, such a strategy could have far reaching consequences for COVID-19 vaccine research and the effective control of the COVID-19 pandemic. These issues merit careful consideration.
In Brief | 02 March 2021 The TOPMed genomic resource for human health
The TOPMed consortium report whole-genome sequencing data from 53,831 ethnically diverse participants. They describe the key features of the genetic variation and produce data resources for future medical research by the wider scientific community.
Darren J. Burgess
Comment | 05 March 2021 COVID-19 vaccines: modes of immune activation and future challenges
This Comment outlines how the recently licensed vaccines for COVID-19 activate innate immune mechanisms to promote immune memory to SARS-CoV-2. The authors also consider future challenges that could limit vaccine efficacy.
John R. Teijaro & Donna L. Farber
Comment | 12 March 2021 Signals of hope: gauging the impact of a rapid national vaccination campaign
Preliminary data from Israel demonstrate real-life effectiveness of their COVID-19 vaccination campaign and provide insights that could inform rollout in other countries.
Smadar Shilo, Hagai Rossman & Eran Segal
Original Articles Brief Report: Ebola Virus Transmission Initiated by Relapse of Systemic Ebola Virus Disease
Placide Mbala-Kingebeni, M.D., Ph.D. et al Summary
During the 2018–2020 Ebola virus disease (EVD) outbreak in North Kivu province in the Democratic Republic of Congo, EVD was diagnosed in a patient who had received the recombinant vesicular stomatitis virus–based vaccine expressing a ZEBOV glycoprotein (rVSV-ZEBOV) (Merck). His treatment included an Ebola virus (EBOV)–specific monoclonal antibody (mAb114), and he recovered within 14 days. However, 6 months later, he presented again with severe EVD-like illness and EBOV viremia, and he died. We initiated epidemiologic and genomic investigations that showed that the patient had had a relapse of acute EVD that led to a transmission chain resulting in 91 cases across six health zones over 4 months. (Funded by the Bill and Melinda Gates Foundation and others.)
Articles Societal Costs of a Measles Outbreak
Jamison Pike, Alan Melnick, Paul A. Gastañaduy, Meagan Kay, Jeff Harbison, Andrew J. Leidner, Samantha Rice, Kennly Asato, Linda Schwartz, Chas DeBolt
Pediatrics, Apr 2021, 147 (4) e2020027037
PNAS – Proceedings of the National Academy of Sciences of the United States of America
March 30, 2021; vol. 118 no. 13 https://www.pnas.org/content/118/13
https://stm.sciencemag.org/ The PRISMA 2020 statement: an updated guideline for reporting systematic reviews
Authors: Matthew J. Page, Joanne E. McKenzie, Patrick M. Bossuyt, Isabelle Boutron, Tammy C. Hoffmann, Cynthia D. Mulrow, Larissa Shamseer, Jennifer M. Tetzlaff, Elie A. Akl, Sue E. Brennan, Roger Chou, Julie Glanville, Jeremy M. Grimshaw, Asbjørn Hróbjartsson, Manoj M. Lalu, Tianjing Li…
Citation: Systematic Reviews 2021 10:89
Content type: Research
Published on: 29 March 2021
Open Access Article COVID-19 Vaccine Hesitancy among Young Adults in Saudi Arabia: A Cross-Sectional Web-Based Study
by Dalia Almaghaslah, Abdulrhman Alsayari, Geetha Kandasamy and Rajalakshimi Vasudevan
Vaccines 2021, 9(4), 330; https://doi.org/10.3390/vaccines9040330 – 01 Apr 2021 Abstract
Ending the COVID-19 pandemic requires achieving herd immunity, either by previous infection or by vaccination. However, concerns about the COVID-19 vaccine are growing around the globe. The current study was conducted to investigate young the adult population’s hesitancy towards the vaccine. The study [
Open Access Review The Implementation of Mass-Vaccination against SARS-CoV-2: A Systematic Review of Existing Strategies and Guidelines
by Tasnim Hasan, Justin Beardsley, Ben J. Marais, Thu Anh Nguyen and Greg J. Fox
Vaccines 2021, 9(4), 326; https://doi.org/10.3390/vaccines9040326 – 01 Apr 2021 Abstract
The global drive to vaccinate against severe acute respiratory syndrome-coronavirus-2 (SARS-CoV-2) began in December 2020 with countries in Europe, Middle East, and North America leading the roll out of a mass-vaccination program. This systematic review synthesised all available English-language guidelines and research regarding […]
Media/Policy Watch
This watch section is intended to alert readers to substantive news, analysis and opinion from the general media and selected think tanks and similar organizations on vaccines, immunization, global public health and related themes. Media Watch is not intended to be exhaustive, but indicative of themes and issues CVEP is actively tracking. This section will grow from an initial base of newspapers, magazines and blog sources, and is segregated from Journal Watch above which scans the peer-reviewed journal ecology.
We acknowledge the Western/Northern bias in this initial selection of titles and invite suggestions for expanded coverage. We are conservative in our outlook in adding news sources which largely report on primary content we are already covering above. Many electronic media sources have tiered, fee-based subscription models for access. We will provide full-text where content is published without restriction, but most publications require registration and some subscription level.
The sheer volume of vaccine and pandemic-related coverage is extraordinary. We will strive to present the most substantive analysis and commentary we encounter.
U.S. Florida’s governor bans agencies and businesses from requiring ‘vaccine passports.’
The Biden administration has made clear that it will neither issue nor require so-called vaccine passports, but Republicans have seized on the issue as an example of government overreach.
By Patricia Mazzei, Sheryl Gay Stolberg, Eileen Sullivan and Isabella Grullón Paz
March 29, 2021 News Release New Analysis Indicates U.S. County Vaccination Rates Do Not Correspond to COVID-19 Impact Thus Far
An analysis of Centers for Disease Control and Prevention (CDC) COVID-19 vaccination data from 72% of all counties in the U.S. shows that counties classified as having “low” COVID-19 community transmission (cases and positive tests) levels have an average vaccination rate greater than the rate in counties with “high” community… World Economic Forum [to 3 Apr 2021] https://agenda.weforum.org/news/ Media Accessed 3 Apr 2021
[No new digest content identified]
Vaccines and Global Health: The Week in Review is a weekly digest summarizing news, events, announcements, peer-reviewed articles and research in the global vaccine ethics and policy space. Content is aggregated from key governmental, NGO, international organization and industry sources, key peer-reviewed journals, and other media channels. This summary proceeds from the broad base of themes and issues monitored by the Center for Vaccine Ethics & Policy in its work: it is not intended to be exhaustive in its coverage. You are viewing the blog version of our weekly digest, typically comprised of between 30 and 40 posts below all dated with the current issue date
.– Request anEmail Summary:Vaccines and Global Health : The Week in Review is published as a single email summary, scheduled for release each Saturday evening before midnight (EDT in the U.S.). If you would like to receive the email version, please send your request to david.r.curry@centerforvaccineethicsandpolicy.org.
– pdf version: A pdf of the current issue is available here:
– blog edition: comprised of the approx. 35+ entries posted below.
– Twitter:Readers can also follow developments on twitter: @vaxethicspolicy. . – Links: We endeavor to test each link as we incorporate it into any post, but recognize that some links may become “stale” as publications and websites reorganize content over time. We apologize in advance for any links that may not be operative. We believe the contextual information in a given post should allow retrieval, but please contact us as above for assistance if necessary.
Support this knowledge-sharing service:Your financial support helps us cover our costs and to address a current shortfall in our annual operating budget. Click here to donate and thank you in advance for your contribution.
. David R. Curry, MS Executive Director Center for Vaccine Ethics and Policy
COVAX updates participants on delivery delays for vaccines from Serum Institute of India (SII) and AstraZeneca Statement 03/25/2021 [Editor’s text bolding]
:: The COVAX Facility has notified participating economies that deliveries of doses from the Serum Institute of India (SII) will be delayed in March and April
:: Delays in securing supplies of SII-produced COVID-19 vaccine doses are due to the increased demand for COVID-19 vaccines in India
:: Separately, participating economies in the COVAX Facility that have been allocated doses from the AstraZeneca manufacturing network have been notified that some first deliveries anticipated in March will now take place in April
GENEVA/NEW YORK/OSLO, 25 March 2021 – Deliveries of COVID-19 vaccines produced by the Serum Institute of India (SII) to lower-income economies participating in the COVAX Facility will face delays during March and April as the Government of India battles a new wave of COVID-19 infections. COVAX and the Government of India remain in discussions to ensure some supplies are completed during March and April.
According to the agreement between Gavi and the Serum Institute of India (SII), which included funding to support an increase in manufacturing capacity, SII is contracted to provide COVAX with the SII-licensed and manufactured AstraZeneca (AZ)-Oxford vaccine (known as COVISHIELD) to 64 lower-income economies participating in the Gavi COVAX AMC (including India), alongside its commitments to the Government of India.
To date, COVAX has been supplied with 28 million COVISHIELD doses and was expecting an additional 40 million doses to be available in March, and up to 50 million doses in April.
COVAX has notified all affected economies of potential delays. SII has pledged that, alongside supplying India, it will prioritize the COVAX multilateral solution for equitable distribution.
Participating economies have also received WHO guidance on optimizing the national deployment doses of the AstraZeneca-Oxford vaccine in a constrained supply environment.
Separately, the COVAX Facility has informed participants allocated AstraZeneca-manufactured doses of the AstraZeneca-Oxford vaccine that some of the first deliveries due in March are now set to take place in April.
In this early phase of COVID-19 vaccine roll-out, vaccine manufacturers require time to scale and optimize their production processes. AstraZeneca, which uses a novel supply chain network with sites across multiple continents, is working to enable initial supply to 82 countries through COVAX in the coming weeks.
COVAX retains its objective of supplying initial doses of vaccines to all participating economies in the first half of the year before ramping up significantly in the second half of 2021. To date, COVAX has shipped vaccines to over 50 countries and economies.
::::::
Editor’s Note:
No media release or statement on the manufacturing/supply issues above was identified on the Serum Institute website or the AstraZeneca website.
Gavi Board approves COVAX Buffer for high-risk groups in humanitarian settings
:: 5% of the total number of available doses procured through the COVAX Facility will be allocated to the COVAX Buffer
:: The COVAX Buffer will ensure access to vaccines for populations in humanitarian settings
:: José Manuel Barroso: “While the first resort in covering all high-risk groups, irrespective of their legal status, is including them in national vaccination plans, the COVAX Buffer will serve as a safety net to ensure these populations do not get left behind”
Geneva, 23 March 2021 – The Board of Gavi, the Vaccine Alliance has approved the COVAX Buffer to ensure access to COVID-19 vaccines for high-risk populations in humanitarian settings and enable an emergency release of doses for severe outbreaks. The volume of the COVAX Buffer will be up to 5% of doses procured through the COVAX Facility, thus making up to 100 million vaccine doses available by end of 2021.
While national governments are ultimately responsible for providing access to COVID-19 vaccines for all high-risk groups within their respective territory, the COVAX Buffer will be available for use where there are unavoidable gaps in coverage, for example in instances of state-failure and conflict, and in areas controlled by non-state armed groups inaccessible to governments.
The Inter-Agency Standing Committee (IASC) – a forum of UN and non-UN organisations working to improve the delivery of humanitarian assistance to affected populations – estimates that 167 million people are at risk of exclusion from COVID-19 vaccination. Over two-thirds are in economies eligible for support through the Gavi COVAX Advance Market Commitment (AMC), many in non-government-controlled areas and therefore out of reach of national vaccination campaigns.
“Equitable access is the foundational goal of COVAX, and the available doses should be distributed in accordance with humanitarian principles and upholding governments’ obligations towards populations within their territory,” said José Manuel Barroso, who led his first meeting as a Chair of the Gavi Board. “However, we cannot stop there. While the first resort in covering all high-risk groups, irrespective of their legal status, is including them in national vaccination plans, the COVAX Buffer will serve as a safety net to ensure these populations do not get left behind.”
COVAX Buffer will also provide a contingency for severe outbreaks of COVID-19 by enabling emergency release of doses where regular vaccine allocation timelines may not be sufficient. This surge of doses, aimed at addressing acute outbreaks, is only going to be considered once all COVAX Facility participants have been allocated a base amount of vaccine doses. All COVAX Facility participants, both self-financing and AMC-eligible economies, as well as national and international humanitarian agencies will have access to doses through the COVAX Buffer.
“As we have started the rollout of millions of doses of COVID-19 vaccines to COVAX economies, it is essential to also protect high-risk groups caught in crisis settings,” said Dr Seth Berkley, CEO of Gavi, the Vaccine Alliance. “This means not forgetting the millions of people in conflict-affected settings or in settings that are not under the control of national governments, for it is in these last mile communities where the need for equity is most pronounced.”…
World Bank: WBG Vaccine Announcement– Key Facts
Date: March 23, 2021
COVID-19 vaccines, alongside widespread testing, improved treatment and strong health systems are critical to save lives and strengthen the global economic recovery. To provide relief for vulnerable populations, low- and middle-income countries need fair, broad, and fast access to effective and safe vaccines.
That’s why the World Bank (WB) is building on its initial COVID-19 response with $12 billion to help poor countries purchase and distribute vaccines, tests, and treatments. The first WB-financed operation to support vaccine rollout was approved in January 2021.
Financing:
:: The financing scales up our assistance to help low & middle-income countries procure and get ready to deploy vaccines and strengthen national systems for public health preparedness. This financing is part of the Bank’s initial COVID-19 response announced in April 2020 which is currently supporting more than 110 countries.
:: All Eligible low- and middle-income countries (IBRD/IDA) will be able to access the vaccine financing package within their current lending envelopes for IDA countries and exposure limits for IBRD.
:: The financing package, which is underway and will be rolled out over the next 24 months, helps signal to the research and pharmaceutical industry that people in developing countries need equal access to safe and effective COVID-19 vaccines. Only once the pandemic is contained in all countries will each country be safe from a resurgence.
How it works:
:: The approach draws on the WBG’s significant expertise in supporting large scale immunization programs for vaccine preventable diseases, as well as public health programs to tackle infectious diseases such as HIV, tuberculosis, malaria and neglected tropical diseases.
:: The Bank is working with partners to assess the readiness of countries’ health systems for vaccine deployment and identify gaps and areas for possible investment. This allows Bank financing to support each country’s priority needs. The assessments involve analysis of policy and regulatory capacities, data and tracking systems, health infrastructure including cold chains and training of health workers. Assessments are already underway in more than 140 countries.
:: Developing countries have flexibility to use the financing in ways that best help them, based on their specific context and needs. The financing can be used for the purchasing of vaccines, the distribution of vaccines and strengthening on health systems or a combination of these financing options to meet countries’ vaccine needs.
Vaccine purchase: The WB provides options for vaccine purchase and financing mechanisms including:
– Direct purchases by countries from vaccine manufacturers, either individually or jointly with other countries;
– Purchase of excess stocks from other countries that reserve excess doses;
– Advance purchase mechanisms, such as participating in COVAX. Vaccine distribution: To help countries get ready to deploy vaccines and strengthen their health systems, which are key for effective vaccine distribution, WB financing will be used to establish policies for safe and effective deployment, expand storage and building cold chains, develop data and tracking systems, train health workers and build trust in immunizations through citizen and community engagement. The financing can also be used to purchase and distribute COVID-19 tests and treatments.
IFC’s support on vaccines
Another important part of the World Bank Group’s response comes from IFC, our private sector development arm. The $4 billion Global Health Platform supports private companies in delivering health products and services – including vaccines – to developing countries. This includes:
:: Investments in vaccine manufacturers to foster expanded production of COVID-19 vaccines in low- and middle-income countries, with production reserved for emerging markets.
:: Ability to invest in production to address other potential bottlenecks, including vials, needles and syringes, and cold storage capacity.
:: Support for mapping COVID-19 vaccine manufacturing capacity, focusing on potential bottlenecks in manufacturing processes…
While no one has been spared from the effects of COVID-19, the consequences of this pandemic have not been equally felt. This crisis has been defined by profound and persistent inequities both in terms of who is most at risk, and how the world has responded.
The new Red Cross and Red Crescent analysis released today shows that, although present in all countries, these inequities have been particularly pronounced and damaging for people living in countries affected by humanitarian crises.
According to this analysis: :: Countries that are not dealing with humanitarian crises have reported carrying out nearly 48 times more COVID-19 tests per capita than countries facing “severe” or “very severe” humanitarian crises.
:: People living in countries facing either no humanitarian crisis or crises that are considered “low” in severity are more than three times as likely to be supported with contact tracing for COVID-19.
:: Less than 2 per cent of COVID-19 vaccine doses globally have reportedly been administered in the 32 countries currently facing “severe” or “very severe” humanitarian crises.
Jagan Chapagain, Secretary General of the International Federation of Red Cross and Red Crescent Societies (IFRC), said: “Since the start of the outbreak, we have seen the virus discriminate through its impacts on the elderly, on people with pre-existing conditions, and on people who do not have the economic resources to isolate and protect themselves. What our data shows is that the response to COVID-19 also discriminates. These deep and pervasive inequities mean that, no matter where they are, people in vulnerable settings are more likely than the general population to be infected, are more likely to die once infected, and are least likely to be appropriately supported through the response, including through vaccination campaigns. The same is also true for vulnerable groups in non-crisis settings.”
Robert Mardini, Director-General of the International Committee of the Red Cross (ICRC), said:
“Communities affected by armed conflict have been among the hardest hit by COVID-19, including those who have been displaced, people separated from their families, those deprived of their livelihoods and people in detention. That is why the ICRC is supporting National Societies, vital health infrastructure, access to health care, efforts to prevent the spread of disease in places of detention, access to clean water, and the safe and dignified management of human remains in places experiencing conflict and violence.”
The revised International Red Cross and Red Crescent Movement plan is designed to counter some of the more severe inequities by expanding care, treatment and support for people in all countries, including those affected by humanitarian crises such as conflict and disasters. The plan also includes a range of measures designed to support and extend COVID-19 immunization campaigns so that marginalized and isolated groups — including people living in conflict zones, migrants and displaced people, people living in urban slums, and isolated communities in non-crisis affected countries — can access vaccines.
In all, the revised International Red Cross and Red Crescent Movement appeal seeks 2.729 billion Swiss francs…
Weekly Epidemiological and Operational updates Last update: 23 January 2021 Confirmed cases :: 125 781 957 [week ago: 121 969 223] [two weeks ago: 118 754 336] Confirmed deaths :: 2 759 432 [week ago: 2 694 094] [two weeks ago: 2 634 370] Countries, areas or territories with cases :: 223
::::::
Weekly operational update on COVID-19 – 22 March 2021 Overview In this edition of the Weekly Operational Update on COVID-19, highlights of country-level actions and WHO support to Member States include: :: Calls for maintaining essential health services amid disruptions from COVID-19 pandemic :: The role of traditional leaders for community-based interventions against COVID-19 :: The 1-year anniversary of Partners Platform and the COVID-19 Publication Review Committee :: Support in minimizing risks from mass gatherings, preparing and supporting a COVID-19 vaccine campaign and support to virology laboratories :: The Strategic Preparedness and Response Plan (SPRP) 2021 Operational Planning Guidelines, resource requirements and progress made to continue investing in the COVID-19 response and for building the architecture to prepare for, prevent and mitigate future health emergencies is included. :: Updates on WHO/PAHO procured items, participation in the Unity Studies, and select indicators from the COVID-19 Monitoring and Evaluation Framework
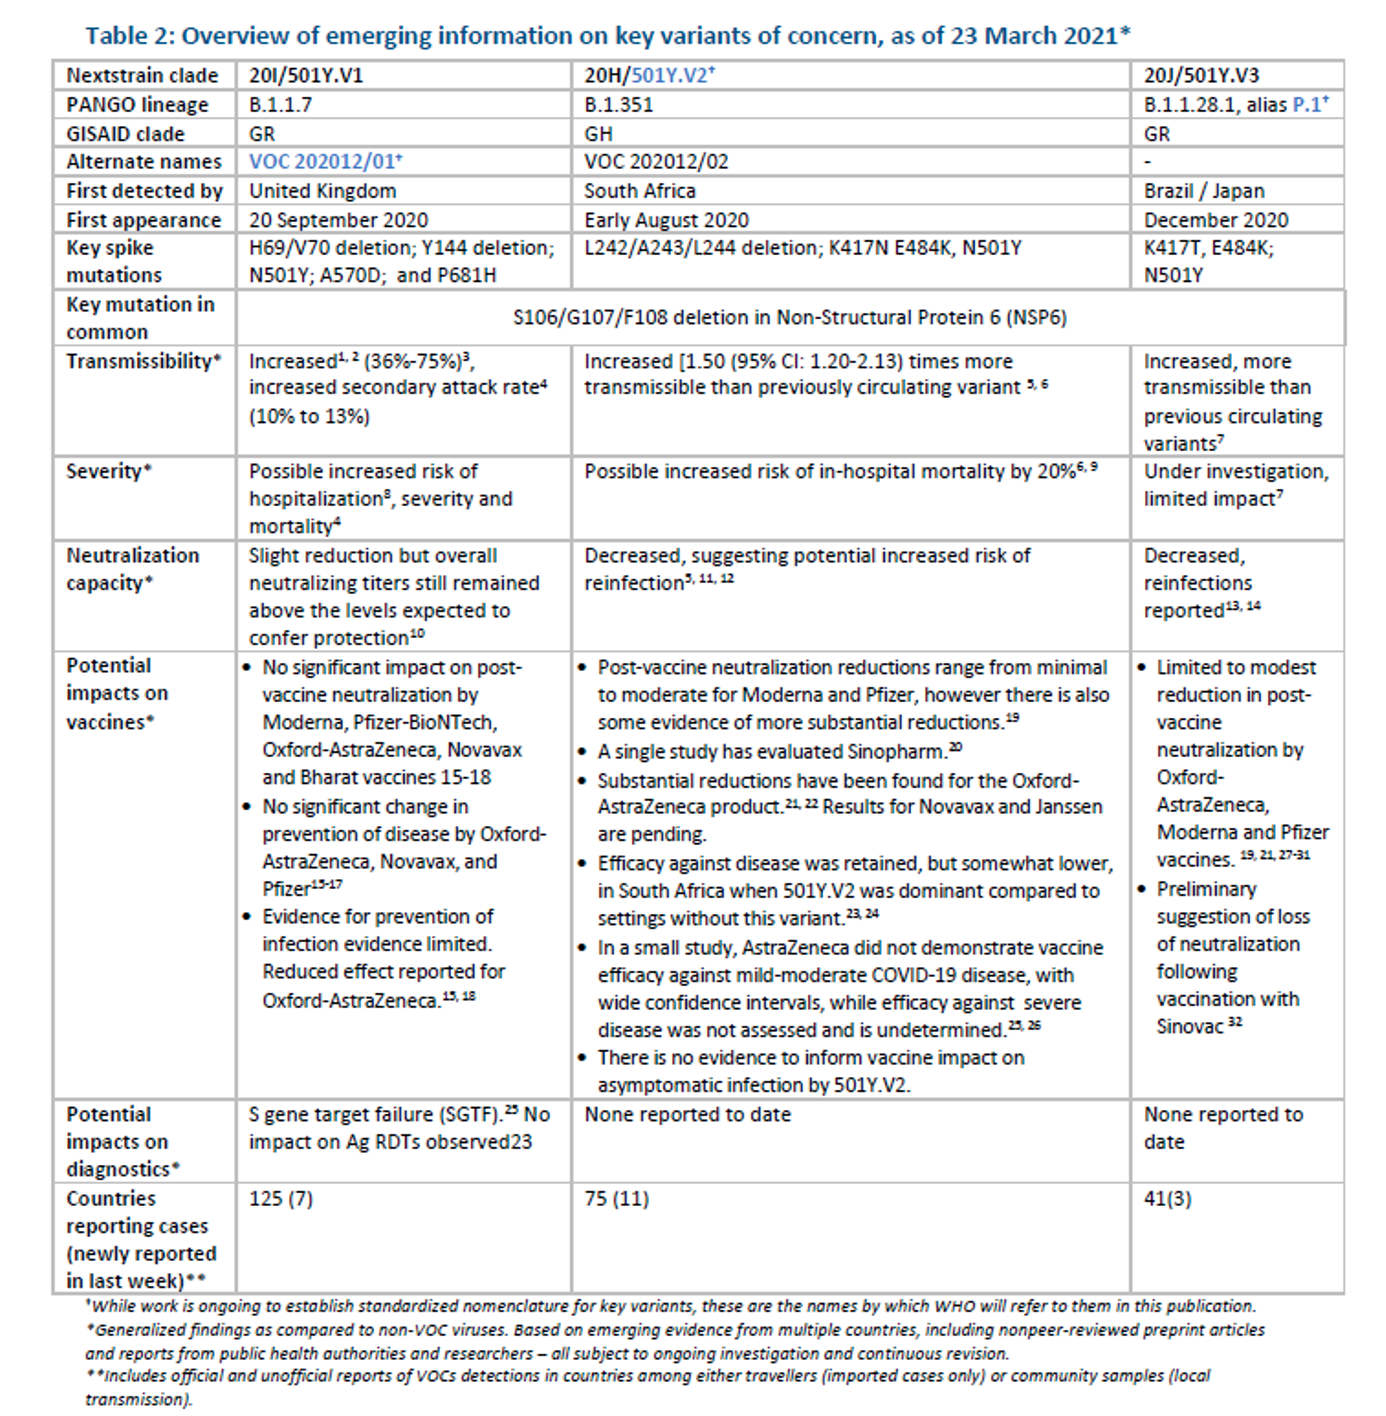
Weekly epidemiological update on COVID-19 – 23 March 2021 Overview Globally, COVID-19 confirmed cases continued to rise for a fourth consecutive week, with just under 3.3 million new cases reported in the last week . Concurrently, the number of new deaths reported plateaued after a six week decrease, with just over 60 000 new deaths reported. A marked increase in the number of new cases was reported from the South East Asia, Western Pacific, European and Eastern Mediterranean regions, all of which are on an upward trajectory in recent weeks. The European Region and the Region of the Americas continue to account for nearly 80% of all the cases and deaths.
In this edition, special focus updates are provided on: :: Release of the WHO COVID-19 Detailed Surveillance Dashboard :: SARS-CoV-2 variants of concern
::::::
::::::
WHO – Feature COVID stories from around the globe 25 March 2021 A virus that respects no borders: protecting refugees and migrants during COVID-19
24 March 2021 Sudan’s community dialogues empower disadvantaged populations to decide on their health priorities
23 March 2021 WHO supports COVID-19 vaccine rollout, highlights women in health and boosts telemedicine during the pandemic thanks to donors
22 March 2021 El Salvador’s President takes the lead in promoting a stringent lockdown against COVID-19 with support from all levels, including the PAHO/WHO country office
Status of COVID-19 Vaccines within WHO EUL/PQ evaluation process 23 Mar 2021 For 16 vaccine candidates, the presents Manufacturer, Name of Vaccine, NRA of Record, Platform, EOI Accepted Status, Pre-submission Meeting Held Status, Dossier Accepted for Review, Status of Assessment; Anticipated/Completed Decision Date [click on the link above for full scale view]
NIAID Statement on AstraZeneca Vaccine March 22, 2021 — Late Monday, the Data and Safety Monitoring Board (DSMB) notified NIAID, BARDA, and AstraZeneca that it was concerned by information released by AstraZeneca on initial data from its COVID-19 vaccine clinical trial. The DSMB expressed concern that AstraZeneca may have included outdated information from that trial, which may have provided an incomplete view of the efficacy data. We urge the company to work with the DSMB to review the efficacy data and ensure the most accurate, up-to-date efficacy data be made public as quickly as possible. Authorization and guidelines for use of the vaccine in the United States will be determined by the Food and Drug Administration and Centers for Disease Control and Prevention after thorough review of the data by independent advisory committees…
New manufacturing site for AstraZeneca’s COVID-19 vaccine A new manufacturing site has been approved for the production of AstraZeneca’s COVID-19 vaccine active substance. The Halix site is located in Leiden, the Netherlands, and will bring the total number of manufacturing sites licensed for the production of the active substance of the vaccine to four.
New manufacturing site and more flexible storage conditions for BioNTech/Pfizer’s COVID-19 vaccine A new site has also been approved for the production of Comirnaty, the COVID-19 vaccine developed by BioNTech and Pfizer. The facility, which is in the German city of Marburg, will produce both active substance and the finished product. There are currently three active substance manufacturing sites supplying the EU included in the marketing authorisation. In addition to the new manufacturing facility for this vaccine, the CHMP has also given a positive opinion to allow transportation and storage of vials of this vaccine at temperatures between -25 to -15˚C (i.e. the temperature of standard pharmaceutical freezers) for a one-off period of two weeks. This is an alternative to the long-term storage of the vials at a temperature between -90 to -60˚C in special freezers. It is expected to facilitate the rapid roll-out and distribution of the vaccine in the EU by reducing the need for ultra-low temperature cold storage conditions throughout the supply chain.
New manufacturing site and scaled-up processes for Moderna’s COVID-19 vaccine Already last week, the CHMP recommended approving the addition of a new manufacturing site for the production of active substance and finished product intermediates for Moderna’s COVID-19 vaccine. The addition of the new manufacturing lines at the Lonza facility, located in Visp, Switzerland, together with other changes to the manufacturing processes that were greenlighted by the Committee are intended to scale-up production capacity and increase supply of the vaccine for the EU market.
The changes described will be included in the publicly available information on these vaccines on EMA’s website…
::::::
European Commission
Remarks by Executive Vice-President Dombrovskis at the press conference on the export transparency and authorisation mechanism and an accelerated approval of adapted vaccines against COVID-19 variants Speech 24 March 2021 … Today, the Commission has adopted an implementing regulation to adapt our export authorisation mechanism for vaccines, with the aim of preserving the security of our supply chains. As you know, the mechanism was introduced on 30 January 2021, and was recently extended until 30 June, with wide support of EU Member States. The system has introduced much-needed transparency in relation to vaccine deliveries in the EU. We have used this mechanism in a balanced way. We have authorised exports on the basis that they did not threaten the commitments undertaken by pharmaceutical companies under their Advance Purchase Agreements. Of 381 requests, 380 have been approved. Only one request for export authorisation was not granted, since it would have compromised the commitments of AstraZeneca. I remind you that AstraZeneca has only delivered a small portion of its agreed contractual commitments. Europe has taken every step to act fairly and responsibly, mindful of our global leadership role, since the start of the pandemic. The EU remains the biggest global exporter of vaccines. We are the largest contributor to low and middle income countries in the so-called COVAX facility. You only have to look at the figures: 43 million vaccines to 33 countries since the end of January. And that only covers the countries which are subject to export authorisation systems. There are many more vaccines going to other countries. No one else has done as much. We see, however, that continuing shortfalls in production are not distributed fairly across different contracting countries. The EU is the only OECD producer that continues to export vaccines to countries that have production capacities of their own. But when these countries do not export to the EU, there is no reciprocity. The EU still faces a very serious epidemiological situation and continues to export significantly to countries whose epidemiological situation is less serious than ours, or whose vaccination roll-out is more advanced than ours. To address these imbalances, President von der Leyen last Wednesday called for reciprocity and proportionality to be introduced in our transparency and authorisation regime. Accordingly, we have today adopted two adjustments to the existing mechanism. These are necessary to achieve our objective of ensuring timely access to COVID-19 vaccines for EU citizens. Going forward, Member States and the Commission should now consider two additional elements when assessing the impact of planned exports. First, reciprocity. If the country of destination, which has a large production capacity, restricts its own exports of vaccines or substances – either by law or other means – it may be appropriate to consider whether exports to this country are justified. The second element is proportionality – which means finding the right balance: Member states and the Commission will consider the conditions prevailing in the country of destination, in particular the epidemiological situation, its vaccination rate and the existing availability of COVID-19 vaccines. Of course, the important consideration to respect Advance Purchasing Agreement remains in place. It is appropriate that we should distinguish between poorly performing companies and well-performing ones that are on track to meet their contractual obligations. In addition, the new act includes some countries, previously exempted, in the scope of the regulation. The primary objective of this adjustment is to have more transparency on exports, and to obtain a full picture on what is happening outside the EU, so as to avoid possible circumvention of the rules. Exports to low- and middle-income countries, supplies through COVAX and exports to EU overseas countries and territories remain unconditionally exempted. The added value of this proposal is that it should allow us to arrive at a more cooperative approach with our partner countries, especially those in a less dire situation. This will also help ensure the well-functioning flow of vaccine and ingredients to give predictability to companies to ramp up global production and safeguard a fair distribution of vaccines. The regulation will help us to meet the expectations of EU citizens, while maintaining our responsibilities to our partners around the world. The most important thing at this crucial moment is to stabilise and accelerate the delivery of vaccines. Thank you.


 vaccines and global health :: ethics and policy
